There is one spot patients point to more than any other. It is not the middle of the low back, and it is not the hip joint itself. It is that deep, nagging area just off to one side, a couple of inches above the belt line and about an inch or two in from the midline, right where the low back starts turning into the pelvis.
Most people find it with a single finger. They press on it, make a face, and say some version of "right here, doc." If that sounds like you, there is a good reason it is so easy to pinpoint, and there is usually a straightforward explanation for why it started.
What Is Actually Under Your Finger
That area is called the lumbosacral junction, and it is the busiest real estate in the entire spine. It is the handoff point where the mobile lumbar spine meets the far more rigid pelvis. Several different structures are packed into a space about the size of a deck of cards:
- The L4-L5 and L5-S1 facet joints. The small paired joints at the back of the spine that guide how you bend and twist. They are richly supplied with pain-sensing nerves.
- The iliolumbar ligament. A thick band running from the bottom lumbar vertebrae out to the rim of the pelvis. Its job is to keep the lumbar spine from sliding and shearing on the sacrum, and it takes a beating when the joints around it stop moving well.
- The top of the sacroiliac (SI) joint. The joint between the sacrum and the pelvis. The dimple you can feel back there is a bony landmark called the PSIS, and the sensitive area often sits just above and inside it.
- Deep stabilizing muscle. The multifidus and quadratus lumborum anchor down into this region, along with the thoracolumbar fascia, the broad sheet of connective tissue that ties your back to your pelvis.
- Small sensory nerves. The superior cluneal nerves cross the crest of the pelvis right in this zone and can get irritated where they pass through tight tissue.
Because these structures overlap, pain from any one of them tends to land in the same small area. That is why the pain is so easy to point to and so hard to describe.
How It Usually Feels
Patients describe this pain in remarkably consistent ways. See how many sound familiar:
- A deep, dull ache that sits there in the background, often compared to a toothache in the back.
- A sharp catch during transitions. Standing up from a chair, getting out of the car, rolling over in bed, or bending to pick something off the floor.
- Worse after sitting still, then easing up after you walk around for a few minutes. Long drives down I-94 or a full day at a desk tend to light it up.
- Worse with one-legged tasks. Putting on socks and shoes, stepping into pants, or climbing stairs.
- Usually one-sided. Many people notice they cannot stand comfortably without shifting weight onto the other leg.
- Spreading, but not far. It commonly wraps into the buttock, the crease of the groin, or the outside of the hip and upper thigh. It typically stops above the knee.
- Stiff in the morning, loosening after 15 or 20 minutes of moving, then returning by evening.
A lot of people live with this for months because it never gets bad enough to stop them. It just quietly takes the enjoyment out of yard work, golf, lifting a toddler, or sleeping through the night.
Why It Starts: Fixation at the Lumbar Spine and Pelvis
Here is the part that surprises people. In most cases, this is not a tissue that is damaged. It is a tissue that is overworked because something next to it stopped doing its share.
Your lumbar spine and pelvis are designed to share motion across many joints. When one segment becomes restricted, a state chiropractors refer to as fixation or joint dysfunction, the motion has to come from somewhere. The neighboring joints and ligaments pick up the slack. Over weeks and months, those overworked structures become irritated, the surrounding muscles tighten up to protect the area, and the guarding makes the original restriction worse. That loop is why the ache tends to hang around and why stretching alone often gives only temporary relief.
Common contributors we see in the office:
- Long stretches of sitting, especially with a wallet in one back pocket or a habitual lean to one side
- Repetitive one-sided work such as shoveling, lifting and twisting, or climbing in and out of a truck all day
- An old ankle, knee, or hip injury that changed how you walk
- Pregnancy and the postpartum period, when ligament laxity and a shifting center of gravity load the pelvis differently
- Flat or unevenly collapsing arches, which change how force travels up from the ground
- A sudden return to activity after a sedentary stretch, which is a familiar story every spring in Macomb County
How This Differs From Sciatica or a Disc Problem
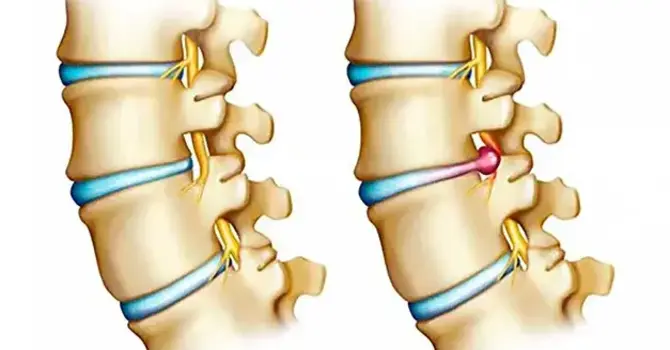
People often arrive convinced they have a disc problem. Sometimes a disc is involved, and that is exactly what an exam is for. But pain that stays in that one spot, is easy to pinpoint with a finger, and does not travel past the knee is more often coming from the joints, ligaments, and muscles of the lumbosacral junction than from a nerve under pressure.
Pain that runs in a line down the back of the leg into the calf or foot, or comes with numbness, tingling, or weakness, points more toward nerve involvement and should be evaluated.
Please seek prompt medical attention if back pain comes with loss of bowel or bladder control, numbness in the saddle region, progressive leg weakness, unexplained fever or weight loss, or if it follows a significant fall or accident. Those findings need to be ruled out before any treatment plan begins.
Why Chiropractic Care Fits This Problem So Well
If the underlying issue is a joint that is not moving the way it should, the logical starting point is restoring that motion. That is precisely what a chiropractic adjustment is built to do. A specific, controlled thrust into a restricted joint restores movement, quiets the protective muscle guarding around it, and takes the excess load off the ligaments and tissues that have been absorbing it.
This is also well supported territory. Major clinical guidelines for low back pain recommend non-drug care, including spinal manipulation, exercise, and hands-on therapy, as a first-line approach before medication or imaging in most cases. For a mechanical problem at the lumbar spine and pelvis, conservative care is generally the appropriate place to start.
Just as important, the adjustment is rarely the whole plan. Restoring motion opens the door. Keeping it open takes work on the soft tissue that has stiffened up and on the muscles that need to hold the correction.
What Care Looks Like at Evolve Chiropractic
Your first visit starts with a conversation and a thorough exam. We test how each segment of your lumbar spine and pelvis moves, check the SI joints individually, screen the hips, look at how you walk and stand, and rule out the findings that would point somewhere other than a mechanical problem. Imaging is ordered when the history or exam warrants it, not as a routine.
From there, care is built around what the exam actually found. Depending on your case, that may include:
- Diversified adjusting and drop table technique to restore motion at the specific lumbar and pelvic segments that are restricted.
- Instrument-assisted adjusting with the Activator or ArthroStim when a lower force, highly specific approach is a better fit, which many patients prefer for a first visit or for an irritated SI joint.
- Graston and IASTM soft tissue work across the iliolumbar region, the thoracolumbar fascia, and the glutes, addressing the tissue that has tightened and thickened around a chronically restricted area.
- KDT Neural-Flex spinal decompression when the exam suggests disc involvement or nerve irritation alongside the joint restriction.
- Webster technique for pregnant patients, a pelvic-focused approach that many expecting moms find helpful for comfort through their pregnancy.
- Custom Foot Levelers orthotics when your arches are part of the reason one side of your pelvis keeps getting overloaded.
- A home exercise program prescribed through Wibbi, with video for each movement so you are never guessing at form between visits.
Four Things That Help Between Visits
- Break up sitting every 30 to 40 minutes. Even standing for a minute changes the load on the lumbosacral junction. This one habit often makes the biggest difference.
- Take the wallet out of your back pocket and notice whether you always stand with weight on the same leg or cross the same knee over the other.
- Walk. Gentle, symmetrical movement is generally better tolerated than aggressive stretching when this area is irritated. Metro Beach and the Clinton River Trail make that easy.
- Hinge at the hips when you lift. Bending through the low back puts the shear right where it hurts.
If the pain is sharp with these, ease off and let us take a look first.
Stop Pointing at That Spot and Let Us Look at It
Pain between the low back and hip rarely resolves on its own once the joints have settled into a restricted pattern, and it rarely needs anything dramatic to turn around either. A careful exam tells us what is driving it, and care starts from there.
Evolve Chiropractic is a solo, doctor-owned practice at 19199 15 Mile Road, Suite B in Clinton Township, serving patients throughout Macomb County including Sterling Heights, Roseville, Fraser, Mount Clemens, and Harrison Township. We accept most major insurance plans.
This article is for general education and is not a substitute for an individual examination, diagnosis, or treatment plan. Results vary from patient to patient. If you have questions about your own back or hip pain, please schedule an evaluation.

Nicholas Duchene
Contact Me